Category Archives: In the News

FDA Proposal Would Lower Requirements for Some Moderate-Risk Devices

Bronwyn Mixter, Bloomberg BNA: March 24, 2017

Over three-hundred class II medical devices made the list of those that might become exempt from premarket notification requirements once the FDA takes final action.

The Food and Drug Administration March 14 published a proposed list of class II devices that will be exempt from the requirements, also called 510(k)s, when the list is made final (82 Fed. Reg. 13,609). Class II devices are moderate-risk devices. A 510(k) clearance demonstrates that a device is substantially equivalent to another (or predicate) device already on the market. Clinical data typically aren’t generated for a 510(k).

The 21st Century Cures Act (Pub. L. No. 114-255), a 2016 law to speed new drugs and devices to market, required the FDA to publish the list. The FDA said the final list will decrease regulatory burdens on the industry by eliminating time and resources needed to submit 510(k) notifications. The devices include dentures, umbilical clamps, obstetrical forceps and surgical clamps. […]

Safety Concerns

The National Center for Health Research, a nonprofit that encourages new and more effective medical treatments, is concerned these devices won’t be reviewed by the FDA.

“We are very concerned about this huge list of devices that will no longer go through any kind of FDA review,” Diana Zuckerman, president of the nonprofit, told Bloomberg BNA in a March 20 email. “The FDA’s faulty justification is that the FDA already knows quite a bit about these devices, but that ignores the fact that when a new company starts making a device, or when any company makes changes to a device, the device can become substantially less safe or substantially less effective, or both.”

Zuckerman said “it is very disturbing that the FDA’s Center for Devices is so focused on relieving device companies of the burden of providing evidence of safety and effectiveness, but not at all concerned that now doctors and patients have an impossible burden of trying to figure out which devices they can rely on and which they can’t. And if we are ever going to have a value-based reimbursement system for medical care, increasingly devices will not be covered because so often there is no scientific evidence that a specific device will benefit patients.” […]


Read original article here.

FDA Agrees With WHO, Links Breast Implants To Rare Cancer. How Worried Should Women Be?

Rita Ruben, Forbes: March 22, 2017

The Food and Drug Administration has received nine reports of women dying of a rare blood cancer years after getting breast implants, according to information the agency released Tuesday.

The FDA says it now agrees with the World Health Organization that such cases are linked to the breast implants and not some unfortunate coincidence. As of Feb. 1, the FDA says, it had received a total of 359 reports of breast implant-associated anaplastic large cell lymphoma (BIA-ALCL).

The FDA reports suggest that implants with a textured surface are more likely to be associated with the cancer than smooth implants—of the 231 reports that contained information about the implant’s surface, 203 were reported to be textured implants, while 28 were reported to be smooth. The Australian Therapeutic Goods Administration (TGA) analyzed 46 confirmed cases of BIA-ALCL, including three deaths, and none of the cases occurred in women with smooth implants.

BIA-ALCL on average is diagnosed about a decade after implant surgery, according to the WHO. The first reported case of a woman with breast implants developing ALCL was published in a 1997 letter to the journal Plastic & Reconstructive Surgery. While that case was a woman with saline-filled implants, the FDA says the filling, be it saline (salt water) or silicone, doesn’t seem to make much of a difference, although no well-designed studies have yet been conducted to settle that issue.

BIA-ALCL is rare, but just how rare isn’t clear. As the FDA notes, it medical device reports can’t answer that question, because they don’t represent all cases, and the denominator—the total number of women who’ve received breast implants—isn’t known.

ALCL is more common in the breasts of women who’ve had implants than in those who don’t have implants, in whom the cancer almost never develops in the breast. A U.S. studypublished in January concluded that over their lifetime, 3.3 women out of every 100,000 with textured breast implants will develop BIA-ALCL. But the TGA estimates that the disease is more common, affecting 1 in 10,000 to 1 in 1,000 women with breast implants (that agency says it has received no reports of BIA-ALCL in women with smooth implants).

“There is no reason to think it is less likely to develop in women in the U.S., and given the dramatic increase in diagnoses in recent years, it is clear that it was under-diagnosed and under-reported for many years,” Diana Zuckerman, a health advocate who has long questioned the safety of breast implants, told me.  Zuckerman serves as president of both the National Center for Health Research and the Cancer Prevention and Treatment Fund, nonprofits based in Washington, D.C. […]

Read the full article here.

Right to Try National Law Would Exploit False Hope

Diana Zuckerman, PhD, Cancer Prevention & Treatment Fund
Published in 19 newspapers including, Chicago (IL) Tribune, Sacramento (CA) Bee, McAllen (TX) Valley Voice, Bellingham (WA) Herald, Cambridge (OH) Sunday Jeffersonian, Lawton (OK) Constitution, Mason City (IA) Sunday Globe Gazette, Willimantic (CT) Sunday Chronicle, New Bedford (MA) Standard Times, Frederick (MD) News Post, and others from March 16-20, 2017

right-to-tryIf you or a loved one were dying of a terminal illness and your doctor told you there were no proven treatments, would you take the risk of trying an experimental, unproven drug?

Many patients would say yes. But as with most medical decisions, the more you know, the more you realize the answer is not so simple.

As has been clearly shown, Congress is not very good at making complicated and nuanced decisions about medical care.

That’s reason enough to question the new federal Right to Try Act dozens of senators and representatives are pushing this spring.

The most important thing to know is that all terminally ill patients already have a right to try experimental drugs in this country.

The proposed new law, however, is much more dangerous to all patients, and not just those facing fatal illness.

Here’s why:

The current national expanded access program enables doctors to request experimental drugs for their patients. If the company that makes the treatment agrees, the patient will get the treatment for free or at cost; companies are not allowed to sell experimental drugs for a profit.

Many patients get access to experimental drugs through this existing program, and improvements are underway to further streamline the process.

In contrast, under the proposed new law, a drug company could charge desperate patients as much as they want to get access to an experimental drug.

Since insurance companies do not pay for experimental treatments, many patients would wind up with the right, but not the money, to try such regimens. Out of desperation, some would surely go into debilitating debt to try a drug that might harm rather than help them.

The current national program makes sure patients understand the risks of taking an experimental treatment and requires that the drug has been studied enough to know that the patient might possibly benefit from it.

Under the proposed new law, drugs that were only studied at a low dose on a small number of healthy volunteers could be sold to patients, and unethical doctors could receive kickbacks for persuading patients to try treatments that will not help them.

It’s easy to understand why every patient wants to have hope of a cure, and that’s the power of right-to-try laws.

So far, hype and false hope have convinced 33 states to pass right-to-try laws that provide no real advantage over the current national program. But rather than learning from the mistakes at the state level, patient activists and others are pushing Congress to pass a much more dangerous federal law.

In addition to encouraging the sale of unproven treatments at sky-high prices to desperate patients, the 2017 federal Right to Try Act would do the following:

  • Allow the sale of almost all experimental drugs, even those never tested on patients before.
  • Prevent patients and family members from suing the company if the treatment harms or even kills them.
  • Prohibit doctors and scientists from evaluating the benefit or harm of the experimental drugs.

Desperate patients are lobbying for the bill, but do they realize what they are lobbying for?

Instead of getting access to free experimental drugs that have some evidence of benefit and are being tested to help all patients, this law would allow naive and desperate patients to be exploited by greedy companies and unethical doctors.

The right-to-try movement opposes the FDA for what’s described as “interfering” with the doctor-patient relationship. They do not understand that unbiased scientific evidence is needed to help physicians and patients make informed decisions – whether to save a life or make a patient’s last months as enjoyable as possible.

Patients already have a right to try through the FDA’s humanitarian expanded access program, which gives them hope while protecting them from greedy exploitation. The proposed federal Right to Try Act would not.

Read original article here.

On the other side of the debate, Naomi Lopez Bauman of the anti-FDA Goldwater Institute wrote a misleading article about why they support a national Right to Try law. 

Let’s set the record straight on at least a few of her misstatements::

  • She claims that companies are prohibited by law from charging more for the investigational treatments than their “actual cost.”  That is true of current law.  However, the national Right to Try Acts that are being considered in Congress specifically allow companies to determine what they will charge for their experimental drugs.
  • She states that in 2015, FDA only allowed 1,300 patients to have access to experimental drugs through their Expanded Access program.  That is true but very misleading, because the FDA is approving 99% of the applications to participate in the program.  The reason the number is low is that when doctors request access for their patients, the companies that are being asked to make their drugs available are not always willing or able to do so.  In some cases, they don’t have enough of the experimental drug available.  In other cases, they believe that the specific patient requesting the drug could be harmed and would not be helped by taking the drug.
  • She states and implies that the national law would not change FDA safeguards and would do no more than make the current state laws national.  That is not true.  On the contrary, the national law would eliminate the role of the FDA from these decisions and the protections that current law provide to prevent patients from being exploited by greedy companies or doctors.
  • She states that “promising new treatments” take more than a decade to be approved by FDA.  We don’t know where that inaccurate statistic comes from, but we do know that the average drug is approved about a year after it is submitted to the FDA, and an article in Cancer World concluded that the FDA approves drugs an average of 6 months faster than the European medical agency
  • She expresses concern that “FDA would retaliate” against those utilizing Right To Try laws.  There is zero evidence to back up that statement.  That is just anti-FDA rhetoric.
  • She states that “most” of the 78 patients treated by an “oncologist” under the Texas Right to Try law “are doing very well,” according to his testimony before a U.S. Senate committee.  If you watch the video of his statement online, you can see the doctor who testified (Ebrahim Delpassand, who is a radiologist, not an oncologist) never said “most are doing very well.” He said that the treatment “has helped many” of the patients, but he doesn’t say how many or to what extent the treatment helped, nor does he say how many were hurt by the treatment.
  • She says something is wrong because “fewer than one-tenth of 1 percent of terminal patients can take advantage of the FDA’s compassionate use exception.”  But the truth is that experimental drugs are just that: experimental and not proven to work or be safe.  Patients can die sooner and in agony from experimental drugs, especially those that have only gone through tiny, preliminary studies of a few healthy volunteers or patients (as the proposed national law would allow).  She neglects to mention that only about 15% of the drugs that complete those preliminary trials are eventually proven to be safe or effective.  The other 85% are either not safe, not effective, or both. That is a very important reason why most patients (and their doctors) do not seek experimental treatments even when they know they can.

Trump’s FDA Nominee Spurs Concerns About Drug Approvals, Off-Label Promotion

Bronwyn Mixter, Bloomberg BNA: March 14, 2017

President Donald Trump’s pick to head the FDA is spurring concerns about drug approvals and off-label promotion.

Trump March 10 nominated Scott Gottlieb to be the commissioner of the Food and Drug Administration. The nomination was widely praised by drug and device industry groups, but a consumer group and other stakeholders told Bloomberg BNA they are concerned that Gottlieb, who is a resident fellow at the American Enterprise Institute and previously worked at the agency as a deputy commissioner, has advocated for quicker drug approvals with less evidence and wants to loosen restrictions on off-label promotion of drugs and medical devices. Critics of the nomination also are concerned that Gottlieb is too closely tied to industry. […]

Gottlieb “is someone who is entangled in an incredible, unprecedented web of ties to industry spanning his professional career,” Public Citizen’s Carome told Bloomberg BNA.

Carome said Gottlieb has been both a venture capitalist and sat on the boards of several drug companies. Gottlieb also “accepted large amounts of money for the period 2012 to 2015, at least $400,000, in speaking fees and consulting fees from several companies and we think it’s just impossible for him to really fully disengage from those ties to industry,” Carome said.

“Like many of President Trump’s other nominees, Scott Gottlieb has extensive financial ties to the industries he’d be in charge of regulating and has shown more interest in reducing regulations rather than enforcing them,” Diana Zuckerman, president of the National Center for Health Research, told Bloomberg BNA in an email.

Zuckerman said “when FDA focuses too heavily on easing the burdens on industry, that shifts the burden to patients, consumers, and physicians” and “none of us can make informed decisions about medical treatments, diagnostics, or prevention strategies when the FDA doesn’t require clear scientific evidence and isn’t transparent about its decisions.”

“If he becomes Commissioner, I hope Dr. Gottlieb will enforce the law and focus on fulfilling the FDA’s essential public health mission,” Zuckerman said. “I expect that industry will strongly support Dr. Gottlieb’s nomination but divesting could potentially be complicated and therefore could delay his confirmation.” […]

Read the full article here.

Statement of Dr. Diana Zuckerman, President, National Center for Health Research, Regarding the American Health Care Act

Diana Zuckerman, PhD, National Center for Health Research, on behalf of Cancer Prevention & Treatment Fund:  March 9, 2017

The goal of the American Health Care Act is to replace the Affordable Care Act (ACA) with something better, but instead it represents a giant step backward for health care for all Americans. This proposed plan will cover far fewer Americans than the Affordable Care Act (ACA), and insurance will pay for less and cost more. The proposed tax credits and Health Savings Accounts (HSAs) will not begin to provide adequate health insurance for Americans covered under the ACA, particularly low-income patients.

A substantial number of people who had health insurance for the first time under ACA will lose it. The proposed 30% surcharge for those who let their insurance lapse is an insufficient incentive for healthy people to purchase insurance. Since the surcharge is the same for patients whose insurance lapses for 2 months or 20 years, it actually discourages healthy patients from buying health insurance until they have substantial medical expenses. The lack of healthy patients in the insurance pool means higher premiums and deductibles for all of us. And, as more uninsured patients end up in hospitals needing expensive medical care for cancer, heart disease, or other serious illnesses, that uncompensated care means higher hospital costs for all of us.

The very obvious shortcomings of the proposed TrumpCare bill are the reasons why hospital organizations, the American Medical Association (AMA), AARP, and many insurers are all against this legislation. It would disrupt the marketplace, create confusion and uncertainty, and reduce or strip health care coverage from millions of Americans.

Meanwhile, the bill would provide tax breaks for the wealthy at the expense of those losing health coverage. The legislation also would serve to severely reduce Medicaid benefits over time, by eventually turning the Medicaid coverage now provided into block grants to states, many of which might spend the funds on issues other than health care.

Trump Picks Scott Gottlieb to Serve as FDA Commissioner

Anna Edney and Robert Langreth, Bloomberg Politics: March 10, 2017

  • Nominee was senior FDA executive under George W. Bush
  • Choice represents mainstream pick for pharmaceutical industry

Scott Gottlieb, a former deputy commissioner of the U.S. Food and Drug Administration, is President Donald Trump’s choice to lead the agency, according to an emailed statement from the White House.

Gottlieb, 44, served in several senior positions at the FDA during the George W. Bush administration. He has talked extensively about how to lower the cost of prescription drugs by modernizing the agency’s approval process and speeding cheaper generic competitors to market.

Since leaving the FDA, Gottlieb has worked as an adviser to investment firms and as a fellow at the conservative-leaning American Enterprise Institute, a Washington think tank. He has been the drug industry’s preferred choice for the FDA job and has worked as a consultant to some of its companies.

Gottlieb must be confirmed by the Senate before he takes over at the agency.

Mainstream Pick

Gottlieb is a more mainstream nominee than some of the other candidates who were said to be under consideration. He’s a partner at one of the world’s largest venture capital firms, New Enterprise Associates, which has a portfolio of more than 300 businesses in the technology and health-care industries, according to its website.

Other names for the FDA post that Trump considered in the past, according to people familiar, were Jim O’Neill, a Silicon Valley investor who has suggested that drugs need to be assessed only for safety, not efficacy, before they’re approved. Another was biotech executive Balaji Srinivasan, who’s tweeted that the FDA “bears responsibility for many deaths” because it “blocked many good drugs.”

While Gottlieb has focused on easing regulations, he “understands the agency and has some respect for it,” Diana Zuckerman, president of the National Center for Health Research, said in an interview before the news that Gottlieb is the leading candidate. The center is a Washington think tank that promotes education and research on policies that benefit patients. […]


Read the full article here.

Amid Flurry of New Cancer Drugs, How Many Offer Real Benefits?

Liz Szabo, Kaiser Health News: February 9, 2017

Marlene McCarthy’s breast cancer has grown relentlessly over the past seven years, spreading painfully through her bones and making it impossible to walk without a cane.

Although the 73-year-old knows there’s no cure for her disease, she wants researchers to do better. It’s been years, she said, since she has found a drug that has actually helped. McCarthy said she’s frustrated that the Food and Drug Administration is approving cancer drugs without proof that they cure patients or help them live longer. […]

Pushed by patient advocates who want earlier access to medications, the Food and Drug Administration has approved a flurry of oncology drugs in recent years, giving some people with cancer a renewed sense of hope and an array of expensive new options. A few of these drugs have been clear home runs, allowing patients with limited life expectancies to live for years.

Many more drugs, however, have offered patients only marginal benefits, with no evidence that they improve survival or quality of life, said Dr. Vinay Prasad, assistant professor of medicine at the Oregon Health and Sciences University, who has written extensively about the FDA’s approval process for cancer drugs.

Overall cancer survival has barely changed over the past decade. The 72 cancer therapies approved from 2002 to 2014 gave patients only 2.1 more months of life than older drugs, according to a study in JAMA Otolaryngology-Head & Neck Surgery.

And those are the successes.

Two-thirds of cancer drugs approved in the past two years have no evidence showing that they extend survival at all, Prasad said.

The result: For every cancer patient who wins the lottery, there are many others who get little to no benefit from the latest drugs. […]

In a November study published in JAMA Internal Medicine, researcher Diana Zuckerman looked at 18 approved cancer drugs that didn’t help patients live longer. Only one had clear data showing that it improved patients’ lives, such as by relieving pain or fatigue.

Two drugs harmed quality of life. For example, thyroid cancer patients taking the most expensive drug, cabozantinib, scored worse on a scale measuring five symptoms: diarrhea, fatigue, sleep disturbance, distress, and difficult remembering, Zuckerman said. […]

“We cannot have a system where drugs that may not even work are being sold for these amazingly crazy amounts of money,” said Zuckerman, president of the National Center for Health Research, a nonprofit in Washington that aims to explain research to consumers.

Recognizing the slow pace of progress, the American Society of Clinical Oncology has set goals for new cancer drugs of extending life or controlling tumors for at least 2.5 months. The bar was set relatively low because “it’s not very often that we come across a transformative treatment,” said Dr. Sham Mailankody, an assistant attending physician and myeloma specialist at Memorial Sloan Kettering.

Yet in a study published in September in JAMA Oncology, Mailankody found that only one in five cancer drugs approved from 2014 to 2016 met those standards. […]

The FDA wants to give patients the chance to benefit as soon as possible, rather than waiting for definitive proof of improved survival, Pazdur said. In some cases, the FDA requires pharmaceutical companies to perform long-term studies after drugs are approved, to measure whether drugs live up to their early promise.

But many of these studies never provide an answer, Zuckerman said. Once a drug is approved and is available to anyone, patients have no incentive to participate in a clinical trial. So studies can end with no clear conclusion. […]

Unless the FDA requires companies to provide survival data before approving a drug, “we may never have answers,” Zuckerman said. “We will have all of these expensive drugs on the market and we will never have the information we need about how well they work or even how safe they are.”

President Donald Trump has vowed to cut regulations at the FDA and recently told pharmaceutical industry leaders that he wants to further speed up the drug approval process. […]

Read the entire article here.

Trump Calls for Lower Drug Prices, Fewer Regulations in Meeting with Pharmaceutical Executives

Carolyn L. Johnson, The Washington Post: January 31, 2017

President Trump met with leaders of some of the world’s biggest pharmaceutical companies Tuesday and emphasized the need to lower “astronomical” drug prices, decrease regulations and bring more drug manufacturing into the United States.

Trump offered no specific policies, but mentioned increasing competition and “bidding wars” as a way to bring down prices. In the past, he has lashed out at the pharmaceutical industry for “getting away with murder” and threatened to use the government’s bargaining power to force down drug prices for programs like Medicare.

Most of Tuesday’s meeting was held behind closed doors, but Trump spoke to the media beforehand while surrounded by executives from a half-dozen large drug companies. He struck a less combative tone and didn’t mention government intervention directly.

“We have to get prices down for a lot of reasons. We have no choice,” Trump said, flanked by chief executives Kenneth Frazier of Merck and Robert Hugin of Celgene. “For Medicare, for Medicaid, we have to get the prices way down.”

In the past, pharma companies have railed against government intervention in pricing, saying those prices fund development of future, lifesaving drugs. […]

There are many empty positions at the FDA, said Diana Zuckerman, president of the National Center for Health Research. The recently enacted 21st Century Cures law provided for additional hiring authority.

“But with the hiring freeze, will they be able to hire anyone?” she asked. […]

Read the complete article here.

After Mastectomies, an Unexpected Blow: Numb New Breasts

Roni Caryn Rabin, The New York Times: January 29, 2017

After learning she had a high genetic risk for breast cancer, Dane’e McCree, like a growing number of women, decided to have her breasts removed. Her doctor assured her that reconstructive surgery would spare her nipples and leave her with natural-looking breasts.

It did. But while Ms. McCree’s rebuilt chest may resemble natural breasts, it is now completely numb. Her nipples lack any feeling. She cannot sense the slightest touch of her breasts, perceive warmth or cold, feel an itch if she has a rash or pain if she bangs into a door.

And no one warned her.

“I can’t even feel it when my kids hug me,” said Ms. McCree, 31, a store manager in Grand Junction, Colo., who is raising two daughters on her own.

Plastic surgeons performed more than 106,000 breast reconstructions in 2015, up 35 percent from 2000. And they have embraced cutting-edge techniques to improve the appearance of reconstructed breasts and give them a more natural “look and feel” — using a woman’s belly fat to create the new breast, sparing the nipple, minimizing scarring with creative incisions and offering enhancements like larger, firmer lifted breasts.

Read the rest of the article here.

2016 study explains why so many cancer drugs don’t work

Diana Zuckerman, PhD, Cancer Prevention & Treatment Fund

Most of us know cancer patients who received drugs that drained their energy and joy of living but didn’t seem to benefit them.  In some cases, the cancer stopped growing within a few months and even began to shrink, but ultimately the patient did not seem to live even a day longer.cancer patient

Why is that?

A key problem is that cancer drugs do not have to be proven to prolong anyone’s life in order for the Food and Drug Administration (FDA) to approve them.  Researchers at the National Cancer Institute and Oregon Health & Science University reviewed all the cancer drugs approved by the FDA from 2008 to 2012 (Kim & Prasad).  They found that 26 of the 54 cancer drugs were not required to be proven to prolong or save lives, but instead were approved based on what are called surrogate markers, which are “signs” such as tumor shrinkage that are expected (but not guaranteed) to predict patients’ longer life.

Once the drugs were approved, thousands of patients started taking these drugs and paying for them, despite the lack of evidence of a meaningful health benefit.  However, the FDA did require the companies to keep studying the drugs to find out if those medicines were actually extending lives.

The answer, unfortunately, is that many of these drugs did not help patients live longer or better.  Only five of the 36 drugs were proven to help patients live longer.  Eighteen drugs (50%) failed to extend life and 13 (36%) have unknown impact on survival because no data on them are available to the public.  Since companies are very good at sharing information when their drugs are proven effective, experts assume that means those 13 drugs are not proven to work.

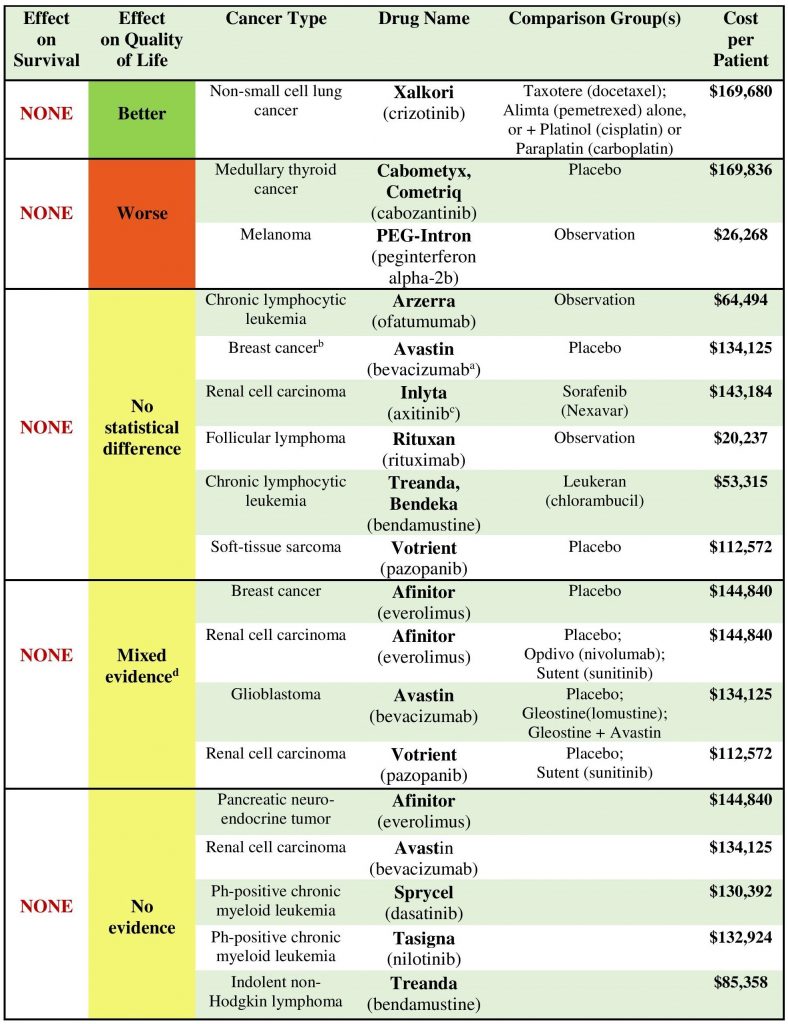
In November 2016, the National Center for Health Research published a study looking more carefully at those 18 ineffective drugs.  We found that only one was proven to improve quality of life – which isn’t surprising, since cancer drugs so often cause nausea, vomiting, hair loss, and exhaustion.  Two made quality of life worse, and the other 15 new cancer drugs either did not improve quality of life (6), or there is not enough evidence to know if they do or not.  We also looked at the cost of those cancer drugs and found something that doctors, patients, family members, and lawmakers need to know:  the new cancer drugs that are not proven to benefit patients in any way cost just as much as the ones that are effective – up to $170,000 per patient.  In fact, the most expensive of the 18 cancer drugs was a thyroid cancer drug (Cabozantinib, also called Cabometyx or Cometriq) that had no benefit to survival compared to placebo, and also caused patients to have a worse quality of life.

Meanwhile, the ineffective cancer drugs remain on the market and Medicare and insurers are still paying for them.  When the president of the National Center for Health Research asked FDA officials why they take so long to rescind the approval of ineffective cancer drugs, they stated that they still think those drugs might be effective, but that it is difficult to prove.  They pointed out that once a cancer drug is approved, it is very difficult to keep patients in a clinical trial long enough to know if the drug actually saves lives.  We agree it is difficult; if a patient is in a clinical trial and not doing well, he or she is likely to drop out, whether they are on the new drug, old drug, or placebo.  But that’s a major problem: if the FDA is approving cancer drugs on short-term, inconclusive data, and then requiring better studies that they know are unlikely to be completed appropriately, that’s quite a Catch-22.  It means that the FDA is approving cancer drugs knowing that we’ll never know if they are safe and effective or not.

This article is based on this study in JAMA Internal Medicine.1

Table 1. Most New Cancer Drugs That Don’t Help Patients Live Longer Also Don’t Improve Their Quality of Life

cancer-drug-table-page-001


a FDA review notes that sponsor stated one study found a difference in deterioration of QoL that was statistically significant in favor of bevacizumab.

b On November 18, 2011, FDA revoked accelerated approval of the breast cancer indication for bevacizumab.

c One subgroup analysis of Japanese patients found a QoL benefit.

d Includes any combination of the other categories (better, no statistical difference, worse).


P.S. In 2019, cancer therapy drug Lartruvo failed to meet the main goal in a late-stage trial testing the therapy in patients with advanced or metastatic soft tissue sarcoma.  Read more here.